FINALLY! An Ad Guaranteed Way to Make YOU $$$

Saturday, August 20, 2016

New MRSA Drug Found In Novel Location - Snot

This may sound strange but it’s snot funny, it’s an exciting potential new source of critically needed antibiotics which has already yielded a way to combat MRSA, a hospital acquired infection which probably kills 100,000 people each year worldwide - 10,000 just in the U.S.

The need for new antibiotics is desperate because overuse and misuse has rendered many drugs useless resulting in killer infections such as MRSA (methicillin-resistant Staphylococcus aureus) which is the target of lugdunin a new drug emerging from, of all things, human snot.

The new drug which appears to be very effective against MRSA is actually produced by another strain of Staphylococcus, unsurprisingly known as S lugdunin.

What is really novel about this drug is where it is found, right in the human body, specifically the nose.

The Nose Knows?


This happened because the nasal passages are actually not a very hospitable environment for bacteria so those which dwell there, including both strains of Staphylococcus, which battle it out for living space.

Researchers knew that about one-third of people have S. aureus in their noses so they wondered why the other two-thirds don’t and it turns out that S. lugdunin produces a chemical which kills the MRSA infection.

(Although S aureus is extremely common, which is why it is often found in hospital settings, it seldom gains a fatal foothold in humans unless they are sick and hence in hospitals.)

“We’ve found a new concept of finding antibiotics,” Andreas Peschel, a bacteriologist at the University of Tübingen in Germany, said on Tuesday at the EuroScience Open Forum, a biennial science and policy meeting. “We have preliminiary evidence at least in the nose that there is a rich source of many others, and I’m sure that we will find new drugs there.”
Peschel and bacteriologist Bernhard Krismer discovered the new drug while looking at why one bacteria predominated in some people and not others.
See the complete report in a recent issue of Science Magazine, one of the peer-reviewed science journals of the AAAS.

Friday, August 19, 2016

CDC Warns Pregnant or Potentially Pregnant Women to Avoid Miami Beach and Miami/Date County

Following a detected spread of infected mosquitoes, the U.S. Centers for Disease Control is warning pregnant women and those who might become pregnant soon to avoid Miami Beach.

Male partners of such women should either avoid sex during the pregnancy or use condoms to prevent sexual transmission of the virus.

CDC Update, "Florida Department of Health has identified two areas of Miami-Dade County where Zika is being spread by mosquitoes. In addition to the previously identified area in the Wynwood neighborhood, there is now mosquito-borne spread of Zika virus in a section of Miami Beach." Miami/Date County map.
 Areas in Miami, FL where Zika virus is being spread by mosquitoes.  See guidance for living in or traveling to this area.

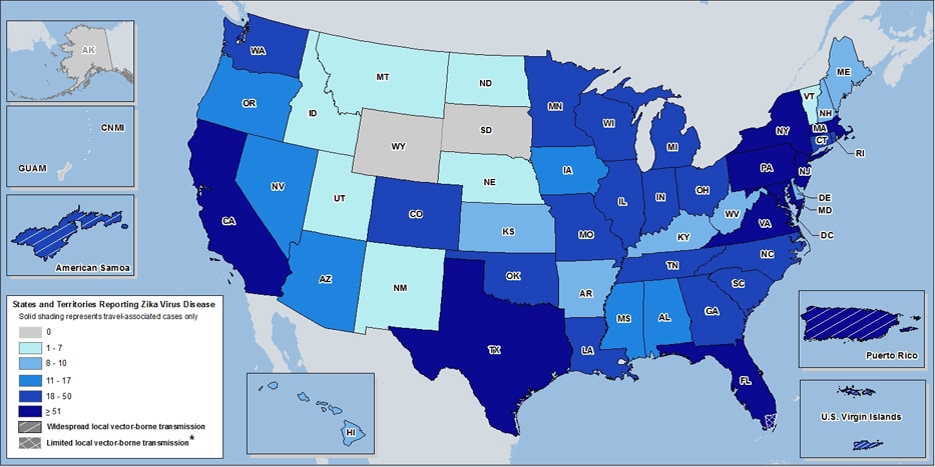
CDC data showing 579 confirmed Zika cases in New York State and even 69 in Pennsylvania and 66 in New Jersey might seem comparable or even worse than the 408 cases reported in Florida, but the raw numbers are misleading - the important number is 14 which is the number of LOCALLY ACQUIRED Zika infections for Florida.

There are NO other locally infected Zika patients in any of the 50 U.S. States, hence no need to warn women to avoid the areas. All of the reported cases outside Florida were people who were infected elsewhere and traveled to those states where the infection was detected in their blood.

See a map and chart at the CDC site for details.

  Map of the United States showing Travel-associated and Locally acquired cases of the Zika virus. The locations and number of cases can be found in the table below.

There are active outbreaks in some U.S. territories which should also be avoided by those who might be pregnant.

American Samoa has 44 locally acquired cases, Puerto Rico has 7,855+, and the U.S. Virgin Islands together have 101 cases.


Wednesday, August 17, 2016

Elder Care Goal - Get Out of Hospital Soonest!

Hospitals are very bad for elderly patients according to recent studies.


Thirty-three percent of patients over 70 and 50+% of those over 85 are more disabled when they leave than when they arrived according to research published in JAMA.

This is hospitalization-associated disability and can occur even when the event which put them in the hospital is cured.

What elderly need most is to eat well, exercise daily, and get plenty of sleep.

Anyone who has ever been in a hospital knows that patients are awoken in the night to take vitals, tied down to beds with IVs, and given food the average cat wouldn’t eat.

Is it any wonder they do badly and so many who were living on their own before entering a hospital go to skilled nursing facilities when they leave, unable to care for themselves ever again?

Doctors' Goals Should be to Treat Less, Rather Than More.


The main goal of doctors treating the elderly should be the opposite of that for treating kids and younger people who usually benefit from bed rest and hospital care.

The elderly, on the other hand, should be released as soon as possible, fed in a room with others, not from a tray in bed, and left to sleep through the night.

They should also be encouraged to walk as much as possible rather than lie in bed even if this means the inconvenience to staff of disconnecting IVs, some of which wouldn’t be needed it the patient exercised and ate decent food.

Simply put, bed rest is BAD for the elderly and just a week confined to bed can do permanent damage which a younger person could simply shake off in a few days at home.

Some hospitals have taken notice of the fact that less care is probably best for the elderly and have set aside special elder care sections where the special needs of elderly patients are addressed.

Thursday, August 4, 2016

ZIKA Weekly SitRep from WHO, the Zika virus has been reported in 68 countries and territories.

See world map at
http://www.who.int/emergencies/zika-virus/situation-report/zika_timeline_2013_2016_v2.JPG?ua=1


Summary

As of 3 August 2016, 68 countries and territories (Fig. 1, Table 1) have reported evidence of mosquito-borne Zika virus transmission since 2007 (65 of these countries and territories have reported evidence of mosquito-borne Zika virus transmission since 2015):

51 countries and territories with a first reported outbreak from 2015 onwards (Table 1).
Four countries are classified as having possible endemic transmission or have reported evidence of local mosquito-borne Zika infections in 2016.

13 countries and territories have reported evidence of local mosquito-borne Zika infections in or before 2015, but without documentation of cases in 2016, or with the outbreak terminated.
The United States of America reported mosquito-borne Zika virus transmission for the first time on 29 July 2016.

Since February 2016, 11 countries have reported evidence of person-to-person transmission of Zika virus, probably via a sexual route (Table 2).

As of 3 August 2016, 14 countries or territories have reported microcephaly and other central nervous system (CNS) malformations potentially associated with Zika virus infection or suggestive of congenital infection. No additional countries or territories have reported microcephaly in the last week. Three of the 14 total countries reported microcephaly cases born from mothers in countries with no endemic Zika virus transmission but who reported recent travel history to Zika-affected countries in the WHO Region of the Americas (Table 3).

As of 3 August 2016, the United States Centers for Disease Control and Prevention (US-CDC) reported 13 live-born infants with birth defects and six pregnancy losses with birth defects with laboratory evidence of Zika virus infection.

As of 3 August 2016, 15 countries and territories worldwide have reported an increased incidence of Guillain-Barré syndrome (GBS) and/or laboratory confirmation of a Zika virus infection among GBS cases (Table 4).

In Guinea-Bissau, on 29 June 2016, Institute Pasteur Dakar (IPD) confirmed that three of 12 samples tested positive for Zika by PC-R. All 12 samples tested negative against IgM Zika. One additional sample from a recent case also tested positive for Zika virus infection. All four samples were sent to IPD on 1 July for gene sequencing and the results are pending. Twenty-two additional samples were collected and sent for testing; the results are still pending.

A roster of WHO technical and communication officers is available to answer media queries during the Olympics.

WHO has developed advice and information on diverse topics in the context of Zika virus. ,

Monday, August 1, 2016

Zika outbreak in north Miami,CDC issues travel warning

CDC issues travel guidance related to Miami neighborhood with active Zika spread

New assessments of mosquito populations and test results this past weekend by Florida public health officials, as part of a community survey in the Miami neighborhood where several Zika infections were recently confirmed, have found persistent mosquito populations and additional Zika infections in the same area. This information suggests that there is a risk of continued active transmission of Zika virus in that area. As a result, CDC and Florida are issuing travel, testing and other recommendations for people who traveled to or lived in the Florida-designated areas on or after June 15, 2016, the earliest known date that one of the people could have been infected with Zika. At Florida’s request, CDC is also sending a CDC Emergency Response Team (CERT) with experts in Zika virus, pregnancy and birth defects, vector control, laboratory science, and risk communications to assist in the response. Two CDC team members are already on the ground in Florida, three more will arrive today, and three more on Tuesday, August 2.

Wednesday, July 27, 2016

Melanoma survival double with both immunotherapy AND local peripheral treatments.

Sciencedaily.com today reported a study and clinical trial which showed that metastatic melanoma patients who received BOTH ipilimumab/Yervoy AND local peripheral treatments had more than double the survival period (93 weeks) of those who only received Yerboy (42 weeks).

This is an especially interesting subject to me because I'm a malignant melanoma survivor from a decade ago and I wrote a booklet about how I survived before these treatments were available,
http://www.amazon.com/John-A.-McCormick/e/B00287RNFS

Back a decade ago there were NO chemotherapy treatments for malignant melanoma which did more than make a very marginal improvement in life expectancy.

I found European clinical studies which showed that Vitamin D-3 more than doubled the survival rate.

There is also considerable evidence that the spice turmeric - often found in curry, also improves your chances of survival.

Since neither of these would in any way interfere with more recent treatments I suggest patients read the scientific results I cite in my book and consider adding Vitamin D-3 and or turmeric to their diets.

My book is the lowest price I could set, 99-cents and Amazon Prime members can read it for free.

Saturday, July 23, 2016

Linus Pauling Vindicated on Vitamin C??Cancer Study Says YES!

Since I only post critical news, rather than attempt a story every day, you might want to subscribe for a feed so you don't miss anything that might save your life. The only limit on postings is that they must be critical news with life-saving potential.

Two time Nobel Laureate Linus Pauling was ridiculed for his suggestion that high dose Vitamin C could fight cancers but recent studies show he may have been on track for a third Nobel for his suggestion.

For ovarian cancer there is an open text study published at www.ncbi.nlm.nih.gov
Two key paragraphs are these found near the end.
“For patients, quality of life is a key issue. In a self-assessment administered to 39 terminal cancer patients treated with 10 g of intravenous ascorbate at 3 day intervals combined with daily administration of 4 g orally for 1 week, quality of life was reportedly improved on several scales. Specifically, patients rated physical, emotional, and cognitive function higher and several symptoms, including nausea, vomiting, loss of appetite, and fatigue, lower after ascorbate treatment. Similarly, advanced cancer patients in the phase I trial who received intravenous ascorbate doses >0.4 g/kg sustained quality of life for the duration of the trial.”
However, neither of these trials had a placebo control. How intravenous ascorbate might mediate improved wellbeing is unknown; further examination with appropriate placebo controls may be worthwhile.
In summary, intravenous ascorbate therapy is safe, well tolerated, and has minimal side effects compared to most standard agents, as verified by both case studies and early clinical trials. Additionally, intravenous ascorbate may contribute to maintaining quality of life.
“Current trials are investigating the potential efficacy of pharmacologic ascorbate given over longer durations in combination with standard chemotherapies.”
Very recent studies just published in Science, the journal of the American Association for the Advancement of Science into the use of Vitamin C in treating two kinds of cancer in rats show very promising results and the same cancer types are found in difficult-to-treat human cancers.
Although the actual study is available only to members, the AAAS provides a summary atsciencemag.org
This study found that colon cancer cells often grow because of mutations in the KRAS or BRAF genes. These cells are fed by high levels of glucose (sugar) but the transporter, GLUT1 also carries Vitamin C to cells as the dehydroascorbic acid (DHA) oxidized form.
Bombarding the cells with high doses of the DHA (Vitamin C) can block free radicals and high doses actually do kill those colon cancers in the lab. The dosages required would require patients eating unbelievable amounts of fruits such as oranges but fortunately the same Vitamin C can be purchased in kilogram packages very inexpensively and mixed with sterile water for IV feeds.

Conclusions?

Since Vitamin C is very cheap and people can not only tolerate it in massive dosages but will probably actually improve their quality of life, it appears that human trials could easily be approved and conducted. Because there is no real safety question, some doctors may agree to give their cancer patients the massive doses along with whatever traditional treatment such as chemotherapy which they are already getting.
I wrote this up before beginning this blog at